

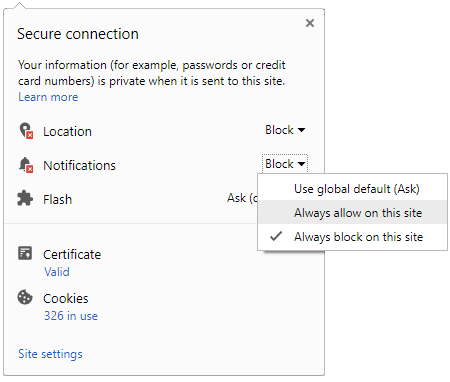
 Click it and Unblock the Notifications
This is What Happened When China Let AI Run An Eye Clinic

A team of researchers in China did not just bolt AI onto an existing eye clinic and call it done. They built one from scratch around the assumption that AI would run most of the workflow, with doctors still in the loop to catch what it got wrong.
The clinic is called AI-TEC, short for AI-Agent Augmented Tsinghua Eye Clinic, and it was set up by a team from the Beijing Visual Science and Translational Eye Research Institute. AI was involved at nearly every stage, from the pre-consultation stage through to reading the actual eye scans and following up with patients afterward. The findings were published in Nature Medicine, and they are a useful reality check on what deploying AI in a real hospital setting actually looks like once the demo phase is over.

The scans got a lot more accurate once the data got better
The AI's early attempts at spotting conditions like glaucoma and age-related macular degeneration in eye scans were not particularly strong. The system had originally been trained on close to 27,000 images, but a lot of that data was low quality and inconsistently labelled.
What changed things was swapping in a much smaller set, just 1,426 scans that had been carefully reviewed and labelled by expert ophthalmologists. That smaller, cleaner dataset pushed accuracy up to an AUROC score of over 0.93, which puts it roughly in line with other leading diagnostic AI systems. The lesson here is a familiar one in AI research, but it is worth restating in a clinical context: quality beats volume when the data is going into something making judgement calls on a patient's eyesight.
Doctors barely used it at first
Accuracy was only half the problem. In a snapshot taken five months into the rollout, staff used the AI-TEC tools in just 41 of 1,113 examinations that month, a little under four percent. That rollout is something most hospitals would call a failure.
The number climbed to 259 out of 1,126 examinations the following month, once the researchers stripped out friction from the workflow, cutting down on clicks and manual data entry that staff had been skipping the tools to avoid. It is a reminder that a clinically accurate model is not the same thing as a usable one, and that clinicians will route around a tool that slows them down, however good its outputs are.
The bigger point
The researchers frame their main finding around three things a system like this needs to work: clean, well-labelled data, a workflow that does not add friction for staff, and fast feedback loops between clinicians and the people building the AI, rather than reviews that arrive weeks after the fact.
There is also a more conceptual gap the paper flags. AI tools tend to work results-first, checking whether a scan shows disease or not. Doctors tend to work symptoms-first, starting from what a patient reports, like blurry vision, and working backward. The researchers suggest that future evaluations of AI-native clinics should weigh whether the tool actually changes patient outcomes and clinical workflow, rather than just how well it scores on a benchmark.
It is a small-scale trial and the researchers are upfront that this is still early, but it is one of the more grounded looks yet at what happens when AI is handed real clinical responsibility rather than just a supporting role.
-
 1,29,999
-
 22,999
-
 64,999
-
 99,999
-
 29,999
-
 39,999
-
-
 63,999
-
 1,56,900
-
 96,949

-
 1,39,900
-
 1,29,900
-
 79,900
-
 65,900
-
 12,999
-
96,949
-
 16,499
-
 38,999
-
 30,700
-
 49,999
-
 19,999
-
 17,970
-
 21,999
-
 13,474
-
 18,999
-
 22,999
-
 19,999
-
 17,999
-
 26,999
-
 5,999


 Continue with Google


